


Effects of GLP-1 Receptor Agonism on Isoproterenol-Induced Cardiomyopathy: Roles of Cardiac Oxidative Stress and the SIRT1/PGC-1α Pathway
- Department of Physiology, Faculty of Medicine, Zonguldak Bülent Ecevit University, Zonguldak, Türkiye
- Faculty of Veterinary Medicine, Bursa Uludağ University, Bursa, Türkiye
- Department of Cardiology, Faculty of Medicine, Zonguldak Bülent Ecevit University, Zonguldak, Türkiye
- Department of Cardiology, Faculty of Medicine, Kastamonu University, Kastamonu, Türkiye
Abstract
Background: A single high dose of isoproterenol (ISO) induces acute cardiac dysfunction with features resembling catecholamine-induced cardiomyopathy and selected aspects of Takotsubo syndrome (TTS), accompanied by heightened oxidative stress. Although glucagon-like peptide-1 (GLP-1) receptor agonists exert established cardioprotective effects, their role in catecholamine-mediated myocardial injury remains incompletely understood. The present study investigated whether liraglutide (LIR) alleviates ISO-induced TTS-like cardiomyopathy in ovariectomized (OVX) rats and explored the potential underlying molecular pathways.
Methods: Surgical menopause was induced in adult female Wistar Albino rats via bilateral ovariectomy six weeks prior to experimentation. Rats were randomized into three groups (n = 8 per group): OVX control, ISO-induced TTS-like cardiomyopathy (single intraperitoneal injection of 150 mg/kg ISO), and ISO plus LIR treatment (150 µg/kg/day subcutaneously for five days before and two days after ISO administration). Cardiac function was evaluated by transthoracic echocardiography at 90 minutes, 24 hours, and 48 hours following ISO administration. Myocardial oxidative and nitrosative stress markers—malondialdehyde (MDA), reduced glutathione (GSH), and nitrate—as well as myocardial sirtuin-1 (SIRT1) and peroxisome proliferator-activated receptor γ coactivator-1α (PGC-1α) protein levels were quantified.
Results: ISO administration induced severe left ventricular systolic dysfunction and ST-segment elevation, accompanied by markedly reduced myocardial SIRT1 and PGC-1α protein expression. In LIR-treated rats, ISO-induced left ventricular systolic dysfunction was significantly attenuated at 48 hours, and myocardial MDA and nitrate levels were significantly reduced compared with the untreated ISO group. Furthermore, LIR treatment significantly restored myocardial SIRT1 and PGC-1α protein expression compared with ISO administration alone.
Conclusion: Pretreatment with LIR is associated with improved left ventricular systolic function in an OVX rat model of ISO-induced TTS-like cardiomyopathy, potentially mediated through the attenuation of myocardial oxidative and nitrosative stress and the preservation of SIRT1/PGC-1α signaling.
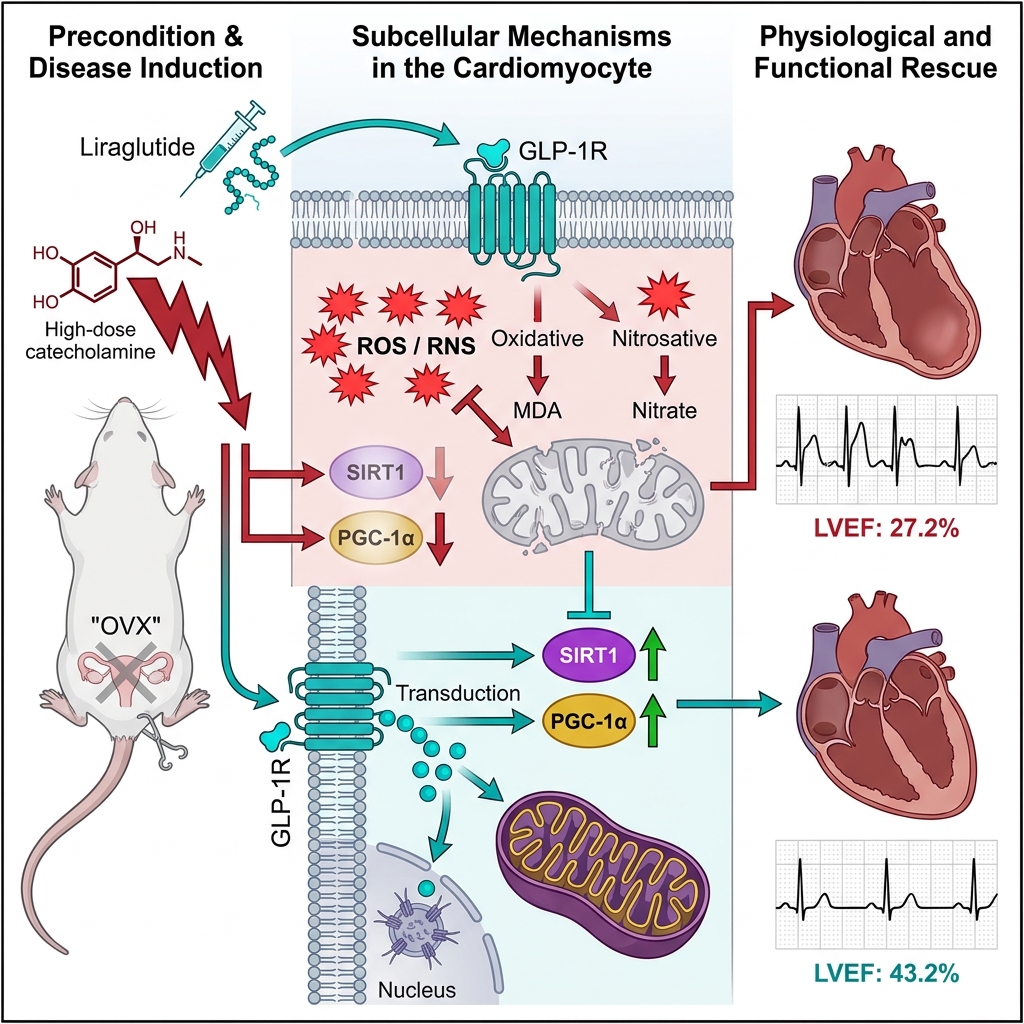
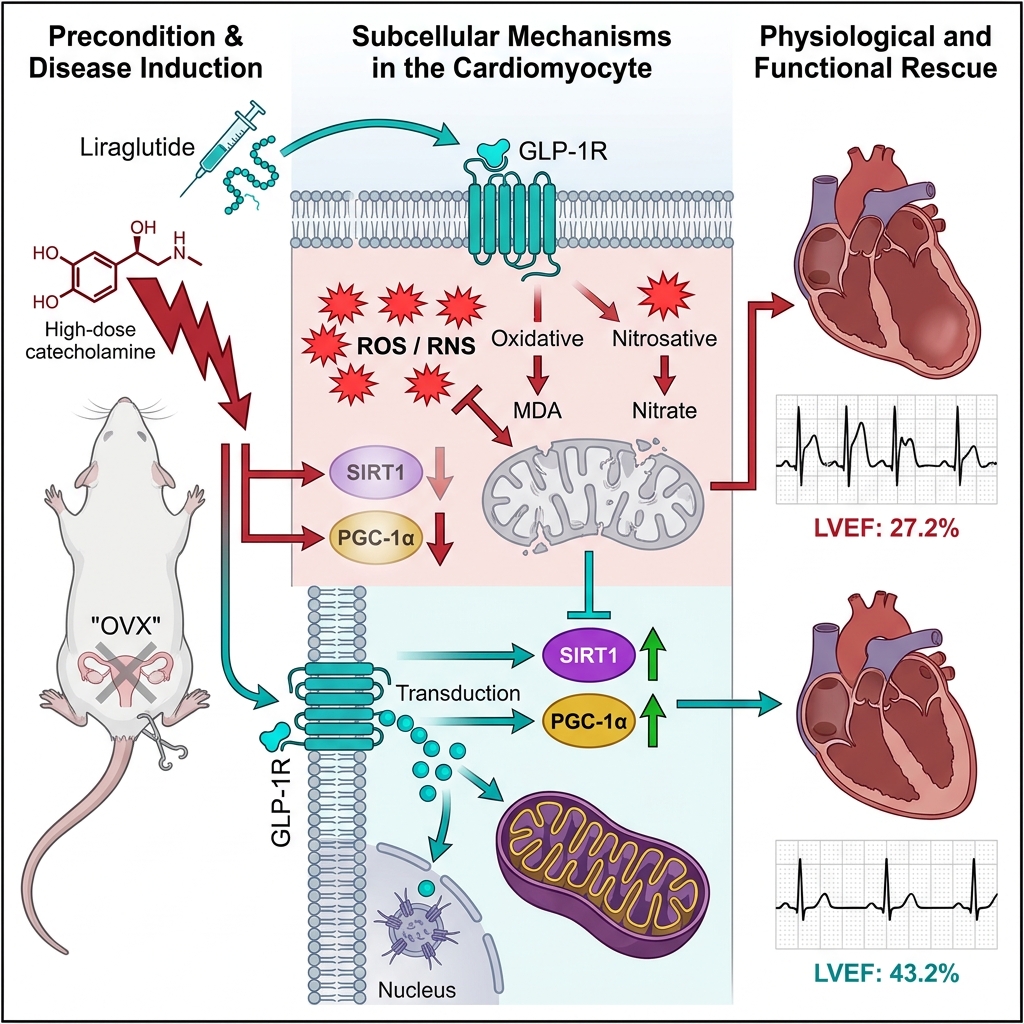
Graphical abstract
Introduction
Isoproterenol (ISO), a synthetic non-selective β-adrenergic receptor agonist, is widely utilized to induce experimental myocardial dysfunction in rodents. High-dose ISO administration produces acute cardiac injury that closely resembles catecholamine-induced cardiomyopathy and shares key pathophysiological features with Takotsubo syndrome (TTS)1. Following an initial surge in heart rate and myocardial contractility, high-dose ISO exposure leads to transient and largely reversible left ventricular dysfunction, mimicking the TTS-like cardiac alterations observed in preclinical models2.
The myocardial injury induced by ISO is primarily attributed to excessive catecholaminergic stimulation and heightened generation of reactive oxygen species (ROS) resulting from catecholamine autoxidation. This oxidative burden promotes membrane lipid peroxidation, inflammatory cascades, and contractile dysfunction3. Clinically, TTS is an acute, stress-induced cardiomyopathy characterized by reversible left ventricular wall motion abnormalities in the absence of obstructive coronary artery disease, typically precipitated by severe emotional or physical stress accompanied by supraphysiological catecholamine levels4. The syndrome classically manifests as acute transient heart failure with distinct regional wall motion abnormalities, most notably apical akinesis or ballooning alongside basal hyperkinesis5.
Notably, TTS predominantly affects postmenopausal women, pointing to a critical role for estrogen deficiency in disease susceptibility. Estrogens confer multifaceted cardioprotection, in part by attenuating sympathetic nervous system overactivation and limiting catecholamine-mediated myocardial toxicity6. Consistent with this paradigm, ISO-induced cardiomyopathy in rodent myocardium is characterized by pronounced oxidative stress and activation of apoptotic signaling pathways1,7. These biochemical alterations include the upregulation of nicotinamide adenine dinucleotide phosphate (NADPH) oxidase subunits, elevated malondialdehyde (MDA) concentrations reflecting lipid peroxidation, and depletion of reduced glutathione (GSH), indicative of compromised endogenous antioxidant defenses8.
Mitochondria represent a primary intracellular source of ROS, and excessive mitochondria-derived oxidative stress is heavily implicated in TTS-like myocardial injury. Preclinical investigations have demonstrated that targeted antioxidant interventions can mitigate mitochondrial ROS generation in stress cardiomyopathy models8. Elevated mitochondrial oxygen free radical production has likewise been documented in ISO-treated rats9. Furthermore, ultrastructural and molecular analyses reveal substantial mitochondrial swelling, diminished adenosine triphosphate (ATP) availability, and downregulation of key proteins governing mitochondrial biogenesis, fusion, and fission during the acute phase of experimental TTS-like cardiomyopathy10.
Peroxisome proliferator-activated receptor γ coactivator-1α (PGC-1α) serves as a master transcriptional coactivator of mitochondrial biogenesis and cellular energy metabolism, playing an essential role in defending the myocardium against oxidative damage11. Downregulated or dysregulated PGC-1α expression is closely linked to the progression of heart failure, whereas preservation of PGC-1α activity sustains mitochondrial integrity and myocardial contractility under pathological stress conditions12.
Sirtuin-1 (SIRT1), a nicotinamide adenine dinucleotide (NAD⁺)-dependent class III histone deacetylase, is another pivotal regulator of mitochondrial homeostasis and cellular stress resistance. SIRT1 exerts potent cardioprotective effects by mitigating oxidative stress and suppressing pro-apoptotic signaling pathways13. Crucially, SIRT1 acts directly upstream of PGC-1α, catalyzing its deacetylation and activation to enhance mitochondrial biogenesis and bolster cellular antioxidant capacity11.
Glucagon-like peptide-1 (GLP-1) is an endogenous incretin hormone integral to glucose homeostasis, and its long-acting receptor agonist liraglutide (LIR) is widely prescribed for the management of type 2 diabetes mellitus and obesity14. Beyond its established glucoregulatory actions, GLP-1 receptor signaling directly modulates cardiovascular physiology, supported by the expression of functional GLP-1 receptors on cardiomyocytes, vascular smooth muscle cells, and endothelial cells15. Experimental evidence indicates that LIR confers direct cardioprotection through antioxidant, anti-inflammatory, and anti-apoptotic mechanisms that operate independently of glycemic control14,16. Although LIR has demonstrated beneficial effects in experimental models of cardiac injury and TTS3,8,16,17,18, its specific impact on myocardial oxidative and nitrosative stress alongside the SIRT1/PGC-1α signaling axis in estrogen-deficient, catecholamine-induced cardiomyopathy remains unexplored. Therefore, the present study aimed to investigate the effects of LIR on myocardial redox status, SIRT1/PGC-1α protein expression, and left ventricular function in an ovariectomized rat model of ISO-induced TTS-like cardiomyopathy.
Materials and Methods
Animals and Experimental Design
Twenty-four healthy adult female Wistar Albino rats (body weight: 290–310 g) were obtained from the Zonguldak Bülent Ecevit University Laboratory Animal Care Unit. Animals were housed under standardized environmental conditions (temperature: 22 ± 3 °C; relative humidity: 50–55%; 12:12-h light/dark cycle) with ad libitum access to standard laboratory chow and tap water. All experimental procedures were approved by the Animal Ethics Committee of Zonguldak Bülent Ecevit University (Approval No. 2024-13-09/05) and conducted in strict compliance with the National Institutes of Health (NIH) Guide for the Care and Use of Laboratory Animals.
Ovariectomy Procedure
Given the marked predominance of TTS in postmenopausal women9, surgical menopause was induced in all rats prior to study initiation. Bilateral ovariectomy was performed six weeks before the experimental protocol under intraperitoneal (i.p.) ketamine/xylazine anesthesia (70 mg/kg ketamine and 10 mg/kg xylazine). Both ovaries were excised via a dorsal midline incision under aseptic surgical conditions. Standardized postoperative care and analgesia were provided, and all animals were monitored daily until complete recovery19.
Experimental Groups and Protocol
Six weeks after ovariectomy, rats were randomly allocated into three experimental groups (n = 8 per group):
-
Ovariectomized control group (OVX): OVX rats receiving vehicle without ISO or LIR administration.
-
ISO-induced TTS-like cardiomyopathy group (ISO): OVX rats receiving a single high dose of ISO to induce acute catecholamine-mediated cardiac dysfunction.
-
ISO plus liraglutide treatment group (ISO+LIR): OVX rats receiving prophylactic and post-insult LIR treatment alongside ISO administration.
Acute TTS-like cardiac dysfunction was induced by a single intraperitoneal injection of isoproterenol hydrochloride (Cat. No. I6504; Sigma-Aldrich, St. Louis, MO, USA) at a dose of 150 mg/kg, as previously established5. Rats assigned to the ISO+LIR group received subcutaneous (s.c.) injections of liraglutide (Saxenda®; Novo Nordisk, Bagsværd, Denmark) at a dose of 150 µg/kg/day for five consecutive days prior to ISO administration, with treatment continuing for two additional days following the ISO challenge (total treatment duration: 7 days)19. This prophylactic regimen was selected based on prior experimental evidence demonstrating that LIR pretreatment effectively attenuates myocardial oxidative injury and preserves cardiac function via GLP-1 receptor–dependent signaling3,16. On day 6 of the protocol, ISO (150 mg/kg, i.p.) was administered to animals in the ISO and ISO+LIR groups. Forty-eight hours after ISO administration (end of day 7), all surviving rats were deeply anesthetized with ketamine (90 mg/kg, i.p.) and xylazine (10 mg/kg, i.p.) and euthanized by exsanguination. The hearts and uteri were rapidly excised, weighed, and snap-frozen at −80 °C for subsequent biochemical and molecular analyses (Figure 1).
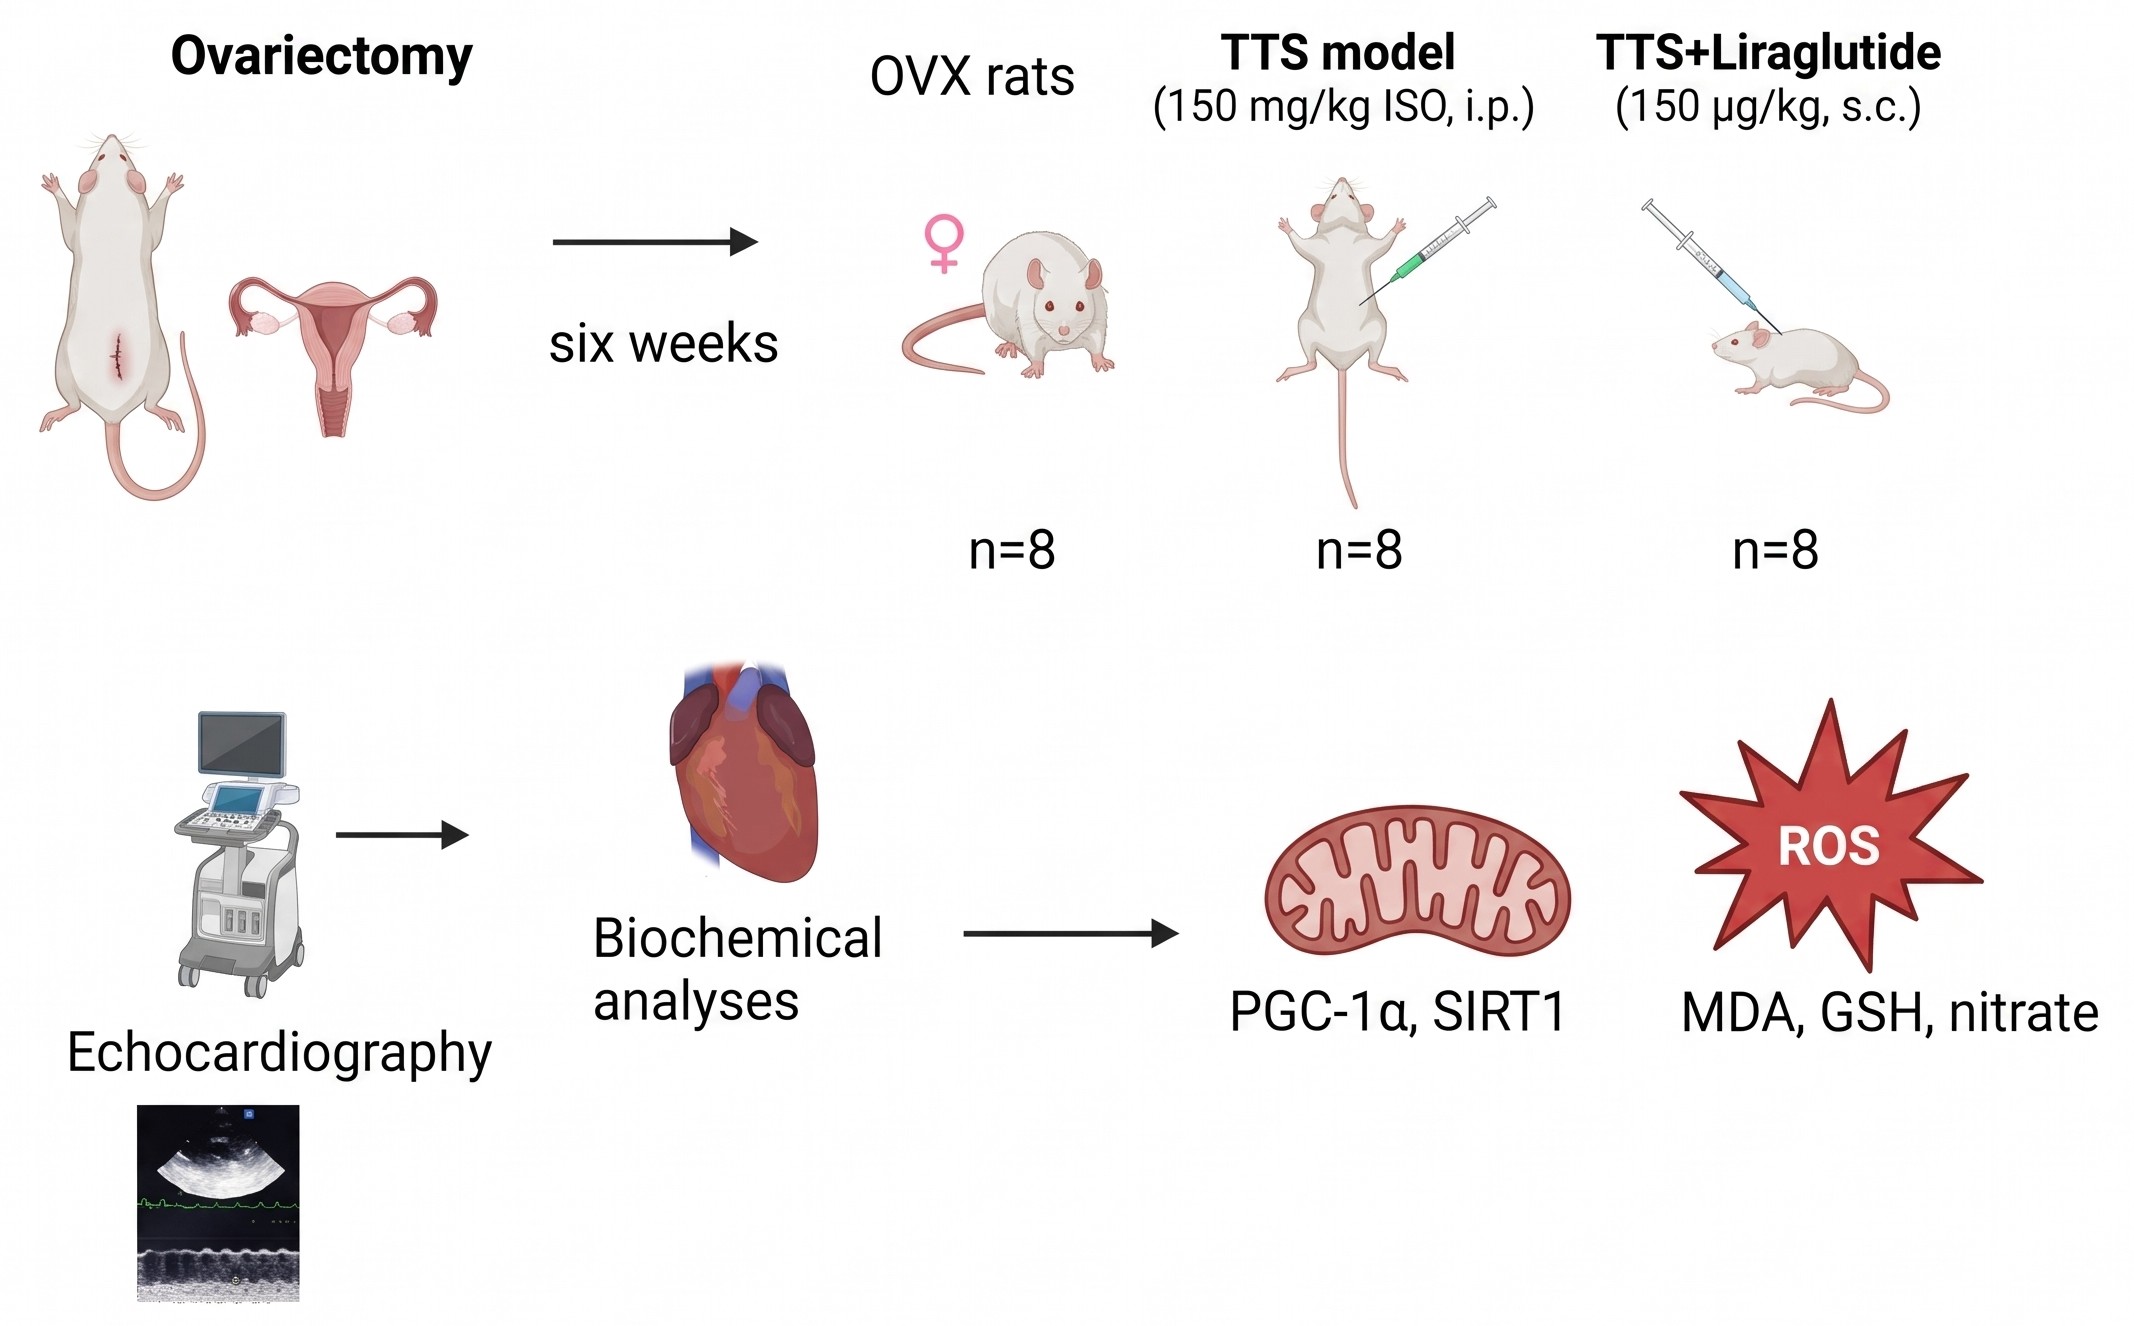
Schematic overview of the experimental design, treatment timeline, and analytical workflow. Adult female Wistar Albino rats underwent bilateral ovariectomy (OVX) six weeks prior to the experimental protocol to induce surgical menopause and were randomly assigned to three groups (initial n = 8 per group): OVX control, isoproterenol (ISO)-induced Takotsubo syndrome (TTS)-like cardiomyopathy (150 mg/kg, single intraperitoneal [i.p.] injection on day 6), and ISO plus liraglutide (LIR) treatment (150 µg/kg/day, subcutaneous [s.c.] injection for five days prior to and two days following ISO administration). Transthoracic echocardiography was performed at 90 minutes, 24 hours, and 48 hours after ISO injection, followed by cardiac tissue harvesting at 48 hours for biochemical quantification of oxidative/nitrosative stress markers (malondialdehyde [MDA], reduced glutathione [GSH], and nitrate) and enzyme-linked immunosorbent assay (ELISA) analysis of mitochondrial regulators (sirtuin-1 [SIRT1] and peroxisome proliferator-activated receptor γ coactivator-1α [PGC-1α]). Abbreviation: ROS, reactive oxygen species.
Transthoracic Echocardiography
Serial transthoracic echocardiographic assessments were performed at 90 minutes, 24 hours, and 48 hours after ISO injection by two experienced investigators blinded to group allocation. Imaging was conducted using a Philips Affiniti 30 ultrasound system equipped with an S8-3 phased-array transducer, accompanied by continuous surface electrocardiogram (ECG) monitoring20. All echocardiographic examinations were performed under ketamine/xylazine anesthesia (70 mg/kg and 10 mg/kg, i.p., respectively). Although ketamine/xylazine anesthesia exerts known negative chronotropic and inotropic effects, identical anesthetic dosing and timing were applied uniformly across all groups to minimize intergroup confounding. Two-dimensional guided M-mode echocardiographic tracings were acquired from the parasternal long-axis view and analyzed offline using the integrated system software. Interventricular septal thickness in diastole and systole (IVSd and IVSs), left ventricular posterior wall thickness in diastole and systole (LVPWd and LVPWs), left ventricular ejection fraction (LVEF), and heart rate (HR) were recorded at each time point (Figure 2).
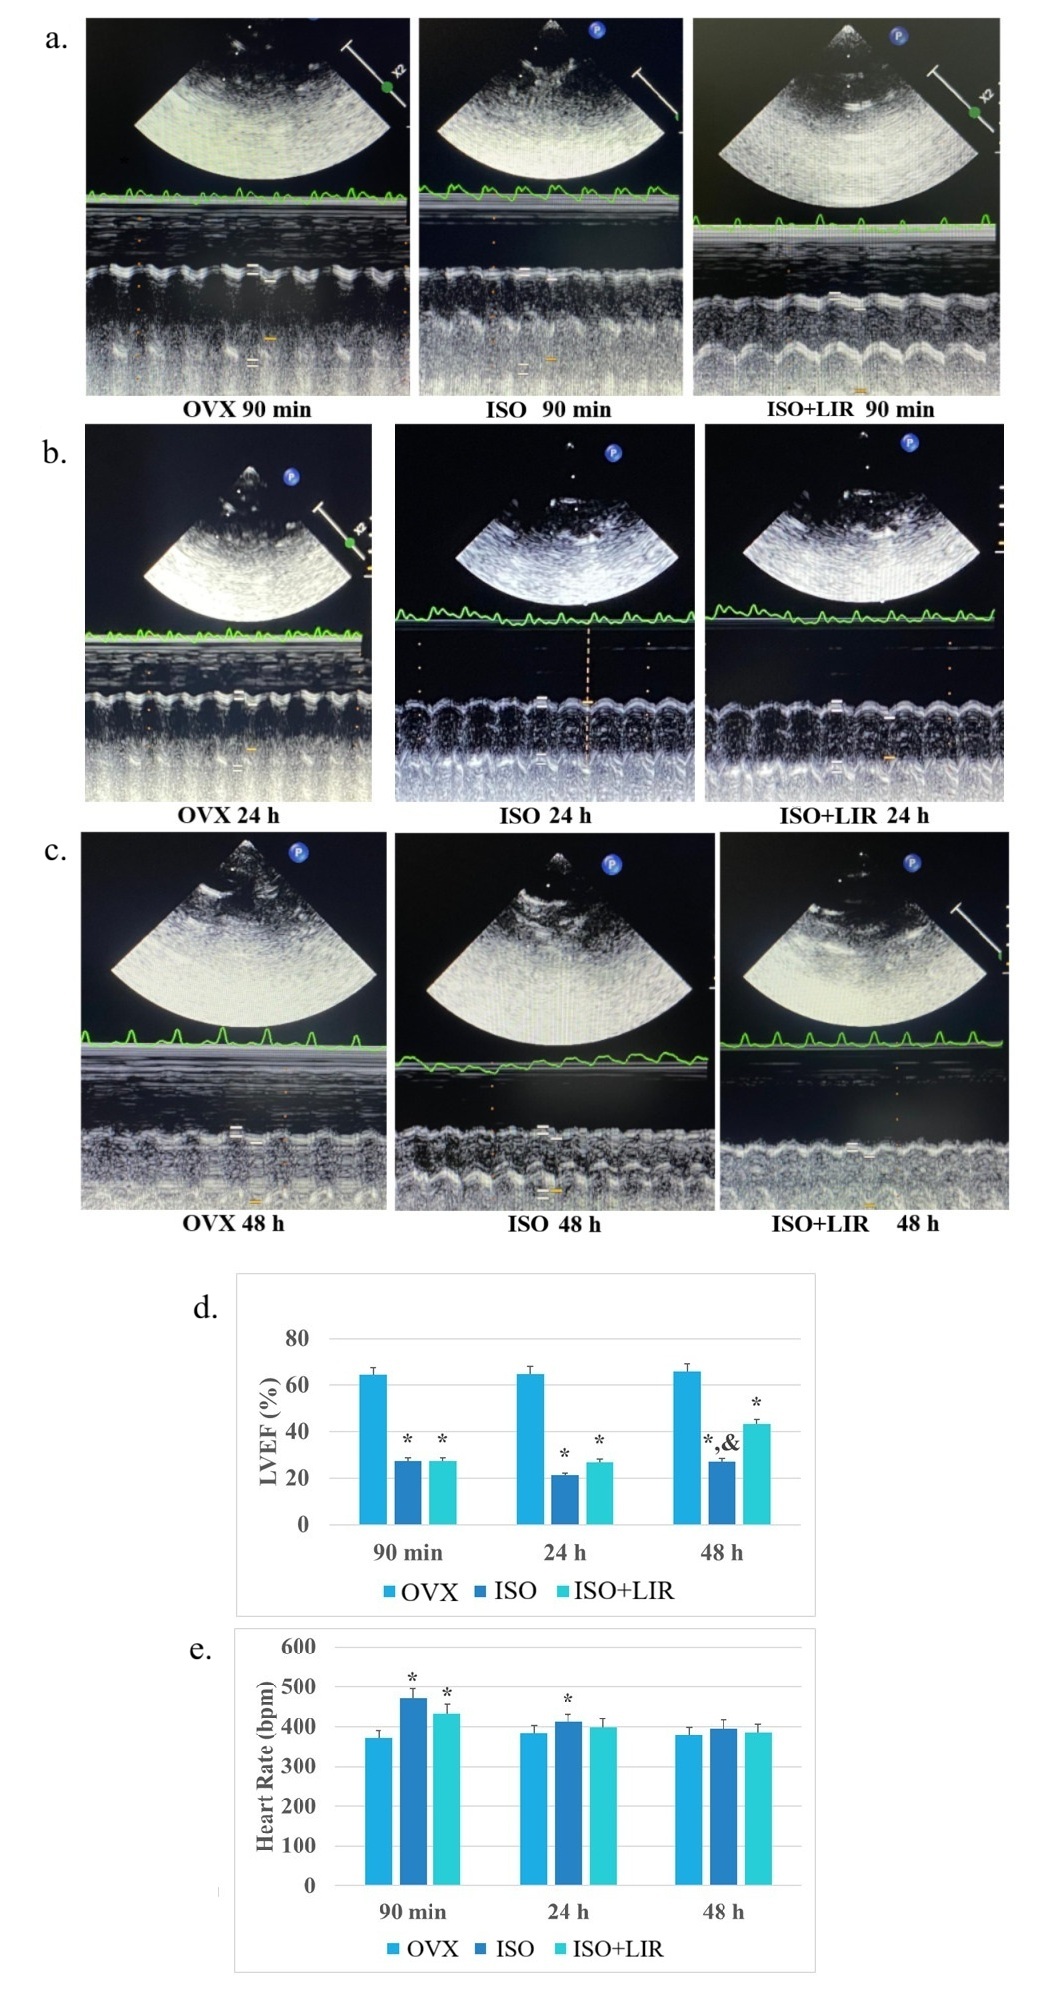
Liraglutide (LIR) treatment attenuates isoproterenol (ISO)-induced left ventricular systolic dysfunction and heart rate elevation in ovariectomized (OVX) rats.(A–C) Representative parasternal long-axis M-mode transthoracic echocardiographic tracings and simultaneous surface electrocardiogram (ECG) recordings (green line) obtained at (A) 90 minutes, (B) 24 hours, and (C) 48 hours following single-dose ISO administration (150 mg/kg, i.p.) in the OVX, ISO, and ISO+LIR groups. (D) Quantitative comparison of left ventricular ejection fraction (LVEF, %) across experimental groups at 90 minutes, 24 hours, and 48 hours post-ISO, demonstrating significant preservation of LVEF in the ISO+LIR group at 48 hours. (E) Quantitative comparison of heart rate (beats per minute [bpm]) at 90 minutes, 24 hours, and 48 hours post-ISO. Bars represent the mean, and error bars indicate the standard deviation (SD) (OVX group, n = 8; ISO group, n = 6; ISO+LIR group, n = 7). Statistical comparisons among groups were performed using one-way analysis of variance (ANOVA) followed by Bonferroni’s post hoc test. *p < 0.05 vs. OVX group; &p < 0.05 vs. ISO group. Abbreviations: bpm, beats per minute; ECG, electrocardiogram; i.p., intraperitoneal; ISO, isoproterenol; LIR, liraglutide; LVEF, left ventricular ejection fraction; OVX, ovariectomized control; SD, standard deviation.
Biochemical Analyses of Myocardial Oxidative and Nitrosative Stress
Myocardial oxidative and nitrosative stress status was evaluated by quantifying tissue malondialdehyde (MDA), reduced glutathione (GSH), and nitrate concentrations. Myocardial MDA levels, an index of lipid peroxidation, were determined spectrophotometrically at 535 nm using the thiobarbituric acid reactive substances (TBARS) method described by Casini et al.21 and expressed as nmol/g tissue. Myocardial GSH levels were measured spectrophotometrically at 412 nm following reaction with 5,5′-dithiobis-(2-nitrobenzoic acid) (DTNB) according to the method of Aykac et al.22 and expressed as µmol/g tissue. Tissue nitrate concentrations, serving as a stable oxidative metabolite reflecting endogenous nitric oxide (NO) production, were quantified at 550 nm using the Griess reaction, with sodium nitrite utilized to generate the standard calibration curve23,24.
Enzyme-Linked Immunosorbent Assay (ELISA) for SIRT1 and PGC-1α
Myocardial SIRT1 and PGC-1α protein concentrations were quantified using rat-specific commercial sandwich ELISA kits (Cat. Nos. ELK6194 and ELK6192, respectively; ELK Biotechnology, Wuhan, China) in accordance with the manufacturer’s instructions. Briefly, excised left ventricular tissues were homogenized in ice-cold phosphate-buffered saline (PBS, pH 7.4) and centrifuged to obtain clear supernatants. Optical density was measured spectrophotometrically at 450 nm, and myocardial SIRT1 and PGC-1α concentrations were interpolated from standard curves.
Statistical Analysis
All quantitative data are expressed as mean ± standard deviation (SD). Intergroup comparisons were performed using one-way analysis of variance (ANOVA) followed by Bonferroni’s post hoc test for multiple pairwise comparisons. A two-tailed p-value < 0.05 was considered statistically significant. All statistical analyses were conducted using IBM SPSS Statistics for Windows, Version 21.0 (IBM Corp., Armonk, NY, USA).
Results
During the seven-day experimental protocol prior to ISO challenge, no overt clinical abnormalities were observed. Following high-dose ISO administration, no mortality occurred in the OVX control group (final n = 8), whereas two rats died in the untreated ISO group (final n = 6) and one rat died in the ISO+LIR group (final n = 7). Animals that succumbed during the post-ISO observation period were included in the echocardiographic analyses up to their last completed assessment time point.
Body Weight, Blood Glucose, Heart Weight, and Uterine Weight
Systemic metabolic and gravimetric parameters—including blood glucose concentrations, body weight trajectories, heart weight, and uterine weight—are summarized in Table 1. Blood glucose concentrations did not differ significantly either among the three experimental groups or within individual groups before and after LIR administration, confirming that the selected 150 µg/kg/day LIR regimen exerted euglycemic cardioprotection16. At the conclusion of the study, final body weight was significantly lower in the ISO+LIR group than in the OVX control group (p < 0.001), accompanied by a significant within-group reduction in body weight compared with baseline pre-treatment values (p < 0.01). No statistically significant differences were observed among the experimental groups with respect to wet heart weight or uterine weight (Table 1).
Effects of liraglutide (LIR) treatment on blood glucose levels, body weight, heart weight, and uterine weight in ovariectomized rats with isoproterenol (ISO)-induced cardiomyopathy.
| Study Variable | OVX (n = 8) | ISO (n = 6) | ISO+LIR (n = 7) | p-value |
|---|---|---|---|---|
| Blood glucose before LIR (mg/dL) | 102.56 ± 3.86 | 96.75 ± 2.75 | 109.2 ± 17.5 | NS |
| Blood glucose after LIR (mg/dL) | 103.87 ± 3.94 | 97.95 ± 2.23 | 104.4 ± 33.7 | NS |
| Body weight before LIR (g) | 310.4 ± 23.5 | 304.1 ± 22.4 | 290.7 ± 19.5 | NS |
| Body weight after LIR (g) | 329.3 ± 27.6 | 311.6 ± 6.87 | 242.5 ± 23.4*ᵃ | *p < 0.001; ᵃp < 0.01 |
| Heart weight (g) | 0.882 ± 0.11 | 1.02 ± 0.118 | 0.922 ± 0.097 | NS |
| Uterine weight (g) | 0.24 ± 0.064 | 0.26 ± 0.09 | 0.322 ± 0.161 | NS |
Echocardiographic and Electrocardiographic Findings in ISO-Induced Cardiac Impairment
Representative M-mode echocardiographic and surface ECG tracings alongside quantitative cardiac parameters recorded at 90 minutes, 24 hours, and 48 hours after ISO injection are presented in Figure 2 (Panels A–E) and Table 2. At both 90 minutes and 24 hours following ISO administration, LVEF was markedly reduced in both the ISO and ISO+LIR groups compared with the OVX control group (p < 0.001; Table 2 and Figure 2D). By 48 hours post-ISO, however, LIR treatment significantly improved systolic recovery, yielding a substantially higher LVEF in the ISO+LIR group (43.2 ± 3.8%) than in the untreated ISO group (27.2 ± 11.2%, p < 0.001), although values remained below those of the OVX control group (65.8 ± 0.15%, p < 0.05; Table 2 and Figure 2D). Additionally, ISO administration significantly reduced diastolic and systolic left ventricular wall thickness parameters (IVSd, LVPWs, and LVPWd) at 90 minutes and 24 hours compared with the OVX control group (p < 0.05 to p < 0.01; Table 2).
Serial transthoracic echocardiographic parameters and heart rate in ovariectomized rats at 90 minutes, 24 hours, and 48 hours after isoproterenol (ISO) administration.
| Study Variable | OVX (n = 8) | ISO (n = 6) | ISO+LIR (n = 7) | p-value |
|---|---|---|---|---|
| LVEF (%) at 90 min post-ISO | 64.4 ± 1.2 | 27.4 ± 6.1* | 27.4 ± 6.1* | *p < 0.001 |
| LVEF (%) at 24 h post-ISO | 64.8 ± 0.72 | 21.2 ± 2.75* | 27.0 ± 3.75* | *p < 0.001 |
| LVEF (%) at 48 h post-ISO | 65.8 ± 0.15 | 27.2 ± 11.2* | 43.2 ± 3.8*& | *p < 0.05; &p < 0.001 |
| IVSs (mm) at 90 min post-ISO | 2.05 ± 0.19 | 1.76 ± 0.10 | 2.07 ± 0.27 | NS |
| IVSs (mm) at 24 h post-ISO | 2.25 ± 0.40 | 1.61 ± 0.36 | 1.93 ± 0.30 | NS |
| IVSs (mm) at 48 h post-ISO | 2.17 ± 0.33 | 1.33 ± 0.06 | 2.13 ± 0.26 | NS |
| IVSd (mm) at 90 min post-ISO | 1.84 ± 0.15 | 1.13 ± 0.22* | 1.37 ± 0.19* | *p < 0.01 (ISO); *p < 0.05 (ISO+LIR) |
| IVSd (mm) at 24 h post-ISO | 1.81 ± 0.17 | 1.08 ± 0.18* | 1.47 ± 0.36 | *p < 0.01 |
| IVSd (mm) at 48 h post-ISO | 1.74 ± 0.44 | 1.38 ± 0.47 | 1.56 ± 0.28 | NS |
| LVPWs (mm) at 90 min post-ISO | 2.23 ± 0.14 | 1.17 ± 0.33* | 1.51 ± 0.44* | *p < 0.01 (ISO); *p < 0.05 (ISO+LIR) |
| LVPWs (mm) at 24 h post-ISO | 2.27 ± 0.28 | 1.27 ± 0.29* | 1.50 ± 0.49 | *p < 0.05 |
| LVPWs (mm) at 48 h post-ISO | 2.29 ± 0.40 | 1.57 ± 0.53 | 1.85 ± 0.53 | NS |
| LVPWd (mm) at 90 min post-ISO | 1.44 ± 0.27 | 0.96 ± 0.06* | 1.01 ± 0.18* | *p < 0.05 |
| LVPWd (mm) at 24 h post-ISO | 1.37 ± 0.46 | 0.91 ± 0.13 | 0.99 ± 0.32 | NS |
| LVPWd (mm) at 48 h post-ISO | 1.42 ± 0.35 | 1.01 ± 0.17 | 1.06 ± 0.29 | NS |
| HR (bpm) at 90 min post-ISO | 371.0 ± 19.0 | 471.7 ± 20.0* | 433.7 ± 25.6* | *p < 0.001 (ISO); *p < 0.05 (ISO+LIR) |
| HR (bpm) at 24 h post-ISO | 384.3 ± 6.0 | 401.2 ± 6.18* | 399.0 ± 8.83 | *p < 0.05 |
| HR (bpm) at 48 h post-ISO | 380.0 ± 5.0 | 396.0 ± 4.3 | 386.7 ± 10.2 | NS |
Although classical left ventricular apical ballooning was not detected on two-dimensional echocardiography in any group, pronounced ST-segment elevation was consistently observed on surface ECG recordings in the untreated ISO group, whereas ST-segment deviations were largely absent in the ISO+LIR group (Figure 2A–C). Heart rate increased significantly at 90 minutes post-ISO in both the ISO and ISO+LIR groups relative to the OVX control group (p < 0.001; Table 2 and Figure 2E). At 24 hours post-ISO, heart rate remained significantly elevated in the untreated ISO group compared with the OVX control group (p < 0.05), whereas heart rate in the ISO+LIR group normalized toward control values (Table 2 and Figure 2E).
Myocardial Oxidative and Nitrosative Stress Markers
As detailed in Table 3, myocardial MDA concentrations showed a numerical increase following ISO administration compared with the OVX control group (49.91 ± 6.5 vs. 47.41 ± 1.6 nmol/g), although this difference did not reach statistical significance. In contrast, LIR treatment significantly decreased myocardial MDA levels in the ISO+LIR group (37.89 ± 8.3 nmol/g, p < 0.05; Table 3). Myocardial GSH concentrations did not differ significantly across the three experimental groups (p > 0.05). Notably, myocardial nitrate levels were elevated in the ISO group (304.6 ± 158.1 µmol/L) but were significantly reduced in the ISO+LIR group (149.0 ± 64.7 µmol/L) compared with both the OVX control and untreated ISO groups (p < 0.05; Table 3).
Effects of liraglutide (LIR) treatment on myocardial oxidative and nitrosative stress markers in ovariectomized rats with isoproterenol (ISO)-induced cardiomyopathy.
| Study Variable | OVX (n = 8) | ISO (n = 6) | ISO+LIR (n = 7) | p-value |
|---|---|---|---|---|
| MDA (nmol/g tissue) | 47.41 ± 1.6 | 49.91 ± 6.5 | 37.89 ± 8.3* | p < 0.05 |
| GSH (µmol/g tissue) | 5.74 ± 0.6 | 5.40 ± 0.43 | 4.90 ± 0.49 | NS |
| Nitrate (µmol/L) | 253.41 ± 95.9 | 304.6 ± 158.1 | 149.0 ± 64.7*& | p < 0.05 |
Myocardial SIRT1 and PGC-1α Protein Expression
Myocardial protein levels of SIRT1 and PGC-1α quantified by ELISA are illustrated in Figure 3. High-dose ISO administration caused a profound reduction in both myocardial SIRT1 and PGC-1α levels compared with the OVX control group (p < 0.05; Figure 3A, B). Conversely, LIR treatment significantly restored myocardial SIRT1 and PGC-1α protein expression in the ISO+LIR group compared with the untreated ISO group (p < 0.05; Figure 3A, B). While SIRT1 expression in the ISO+LIR group recovered toward OVX control levels, PGC-1α expression in the ISO+LIR group remained statistically lower than that of the OVX control group (p < 0.05; Figure 3B).
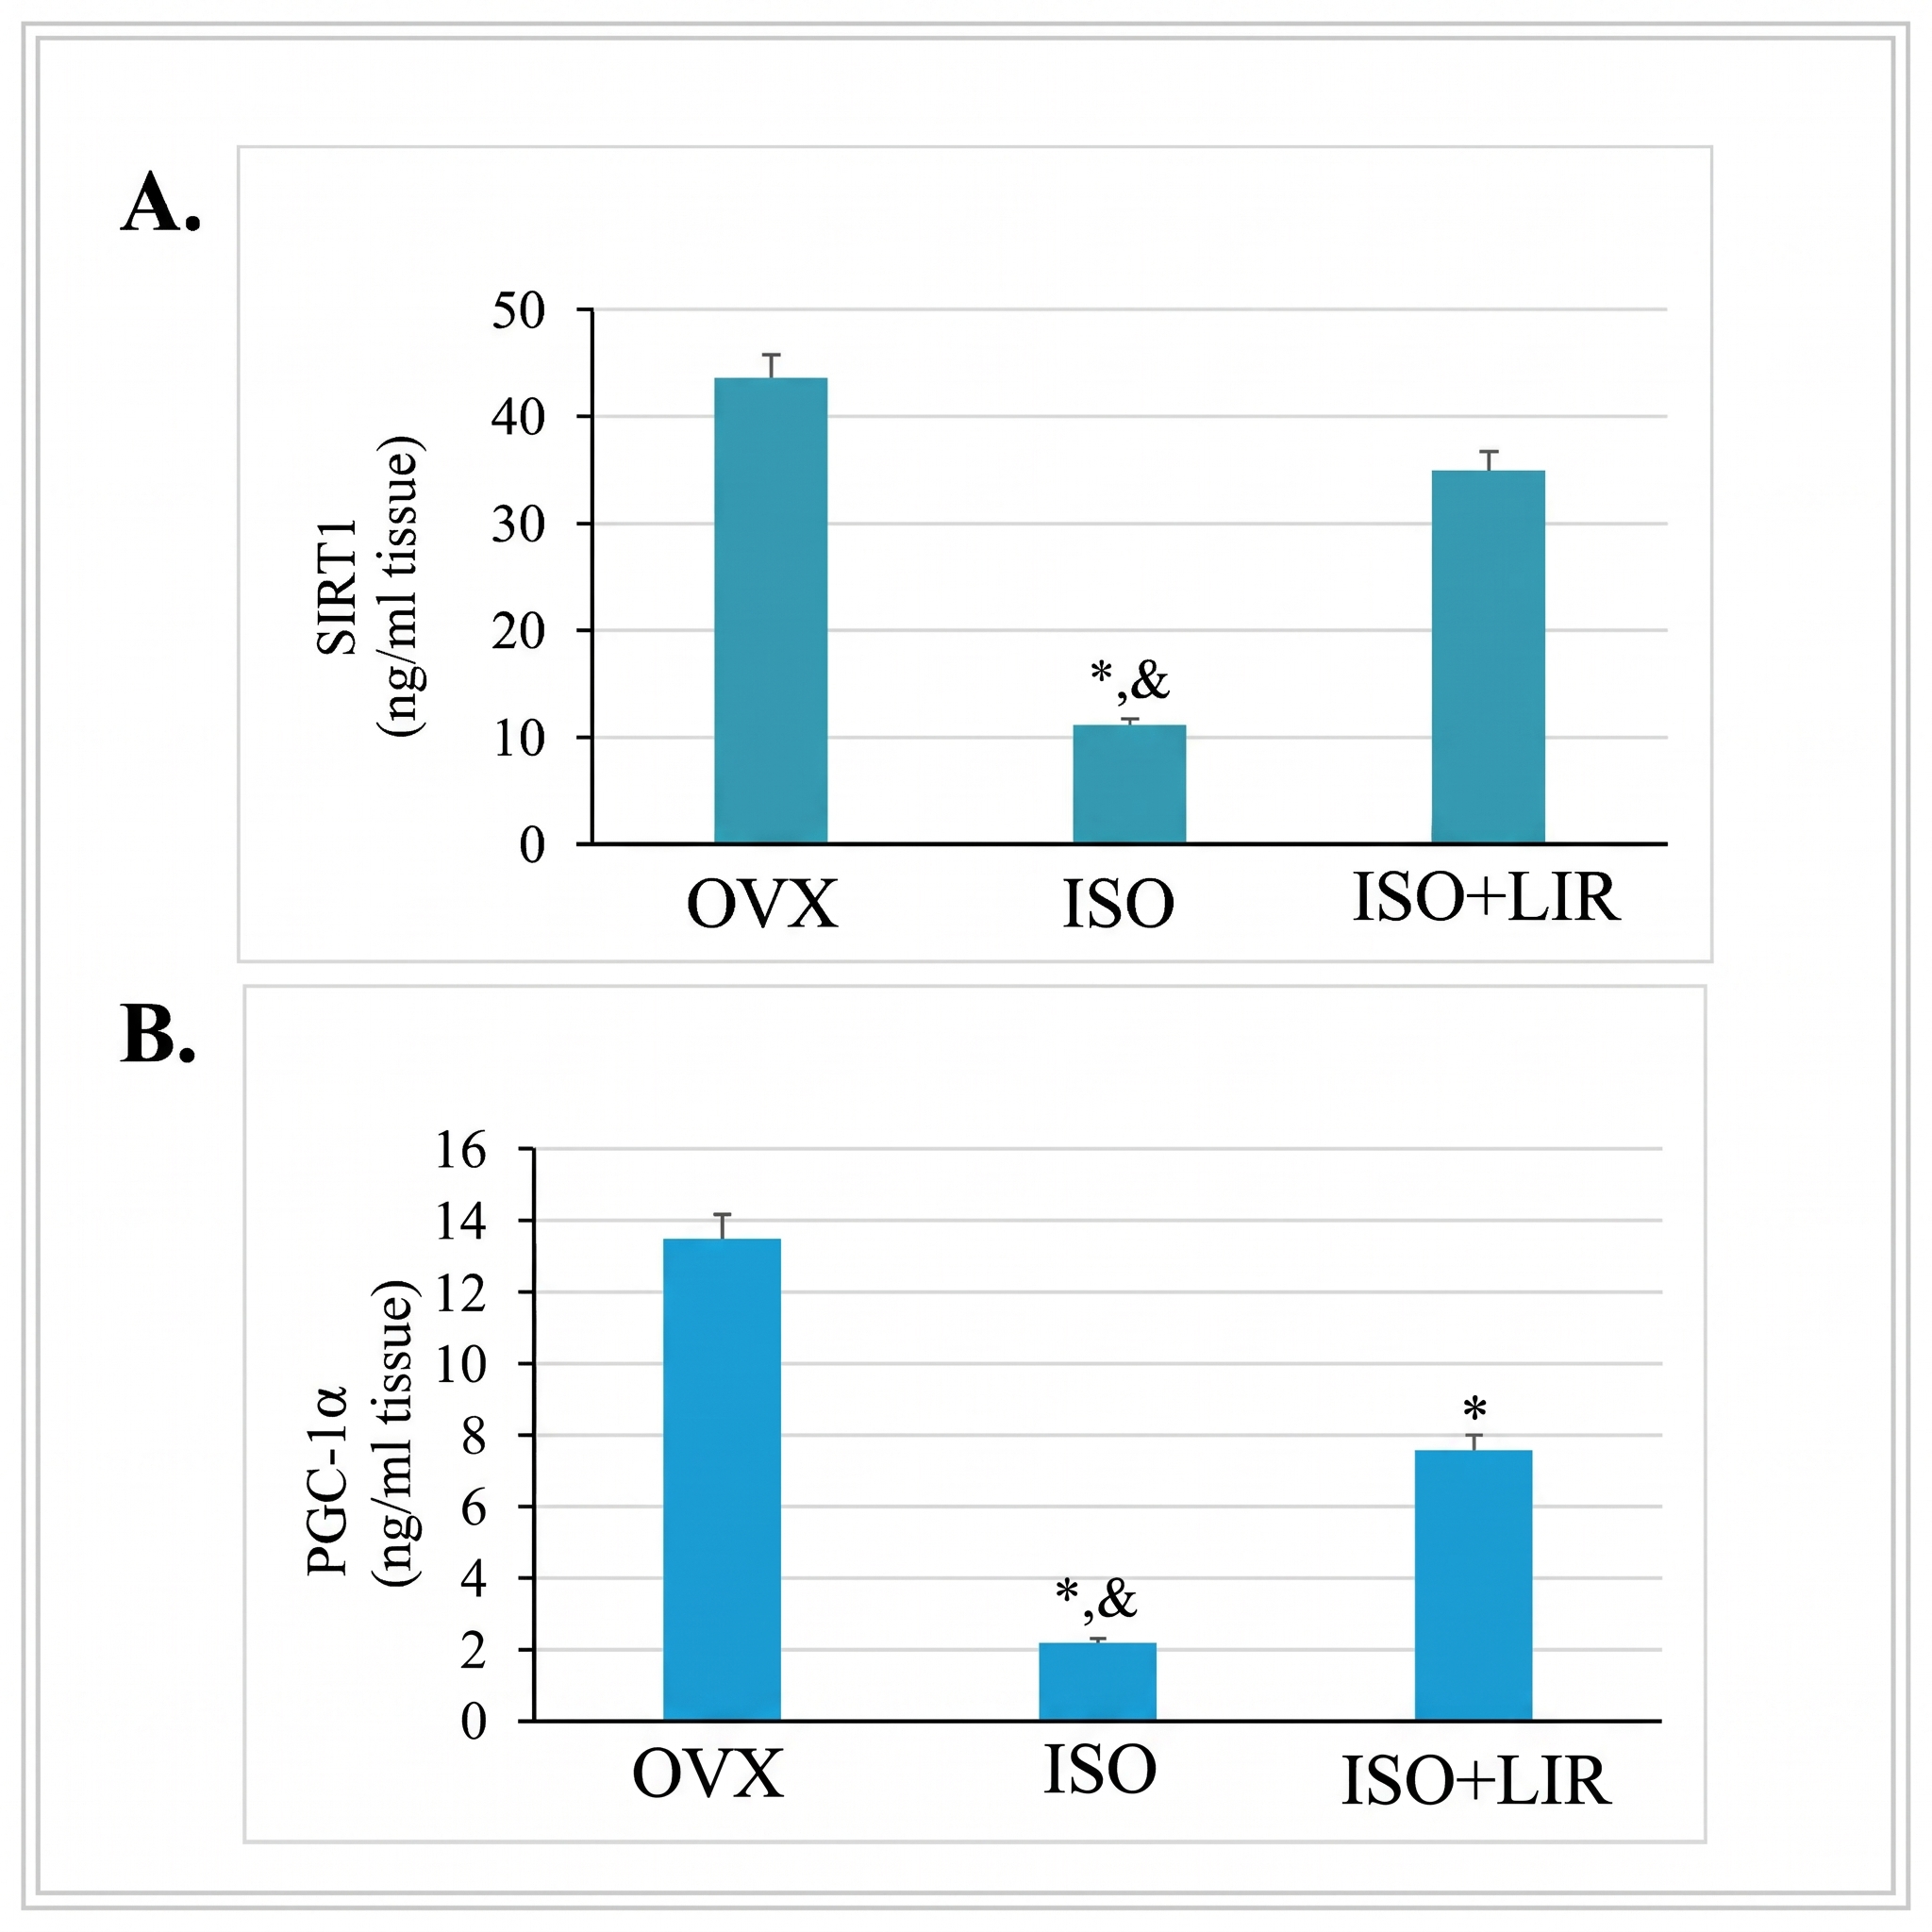
Liraglutide (LIR) treatment restores myocardial sirtuin-1 (SIRT1) and peroxisome proliferator-activated receptor γ coactivator-1α (PGC-1α) protein expression in rats with isoproterenol (ISO)-induced cardiomyopathy.(A) Myocardial SIRT1 protein concentrations and (B) myocardial PGC-1α protein concentrations quantified by commercial enzyme-linked immunosorbent assay (ELISA) in heart tissue homogenates harvested 48 hours after ISO administration. High-dose ISO administration significantly depleted myocardial SIRT1 and PGC-1α protein levels compared with the OVX control group, whereas LIR treatment significantly restored the expression of both proteins compared with untreated ISO rats. Bars represent the mean, and error bars indicate the standard deviation (SD) (OVX group, n = 8; ISO group, n = 6; ISO+LIR group, n = 7). Statistical significance was determined using one-way analysis of variance (ANOVA) followed by Bonferroni’s post hoc test. *p < 0.05 vs. OVX group; &p < 0.05 vs. ISO group. Abbreviations: ELISA, enzyme-linked immunosorbent assay; ISO, isoproterenol; LIR, liraglutide; OVX, ovariectomized control; PGC-1α, peroxisome proliferator-activated receptor γ coactivator-1α; SD, standard deviation; SIRT1, sirtuin-1.
Discussion
In the present study, an ovariectomized rat model of ISO-induced catecholamine-mediated, TTS-like cardiomyopathy was utilized to evaluate the cardioprotective potential of the GLP-1 receptor agonist LIR. Our principal findings demonstrate that a seven-day treatment regimen with LIR (150 µg/kg/day) significantly attenuated myocardial lipid peroxidation and nitrosative stress—as evidenced by decreased myocardial MDA and nitrate concentrations—while upregulating myocardial SIRT1 and PGC-1α protein expression. Crucially, these molecular and biochemical improvements were accompanied by a significant recovery of left ventricular systolic function (LVEF) at 48 hours post-ISO, underscoring a functional benefit of LIR in catecholamine-induced myocardial dysfunction.
Takotsubo syndrome is characterized by acute, transient left ventricular systolic dysfunction typically precipitated by intense emotional or physical stress. Although its precise pathogenesis remains incompletely delineated, sympathetic nervous system hyperactivation and catecholamine surge are recognized as central drivers, supported by clinical observations of markedly higher circulating catecholamine levels in patients with TTS than in those with acute myocardial infarction25. Consequently, ISO—a synthetic non-selective β₁/β₂-adrenergic receptor agonist structurally analogous to epinephrine—is widely employed in preclinical models to recapitulate catecholamine-induced myocardial injury and TTS-like cardiac dysfunction2,3. High-dose ISO provokes myocardial damage primarily through excessive β-adrenergic stimulation, intracellular calcium overload, heightened myocardial oxygen demand, and severe oxidative stress1.
Numerous experimental investigations have confirmed that high-dose ISO administration reproduces hallmark functional, electrocardiographic, and biochemical features of TTS in rodents1,2,4,5. However, gross morphological apical ballooning is inconsistently captured in small-animal models. In the current study, a single intraperitoneal injection of ISO (150 mg/kg) induced profound reductions in LVEF (falling to 27.4% at 90 minutes and 21.2% at 24 hours) alongside marked ST-segment elevation, consistent with severe catecholamine-mediated myocardial stunning. Although discrete apical ballooning was not visualized on transthoracic echocardiography, the absence of this localized geometric feature does not preclude substantial TTS-like myocardial injury. Indeed, multiple studies utilizing comparable ISO dosing protocols have documented severe global systolic dysfunction and TTS-like molecular pathology without overt apical ballooning1, reflecting recognized inter-individual and inter-strain heterogeneity in rodent ventricular remodeling. Moreover, previous investigations have validated the 150 mg/kg ISO dose as highly effective for inducing reproducible TTS-like cardiomyopathy in adult female rats26,27.
The striking epidemiological predominance of TTS in postmenopausal women implicates estrogen deprivation as a key predisposing factor. Under physiological conditions, estrogens preserve coronary endothelial function, modulate autonomic tone, and blunt excessive β-adrenergic signaling. Bilateral ovariectomy is therefore the gold-standard experimental paradigm for modeling postmenopausal hypoestrogenism in rodents. Because a sham-operated (gonadally intact) control group was not included in the present study design, the independent contribution of ovariectomy cannot be isolated from the effects of ISO or LIR; thus, conclusions regarding menopausal susceptibility specifically should be interpreted with caution. Nevertheless, seminal work by Ueyama et al. demonstrated that OVX rats exhibit heightened vulnerability to stress-induced left ventricular dysfunction compared with estradiol-replaced counterparts28. Furthermore, while acute neuroendocrine fluctuations partially stabilize within two weeks after ovariectomy, sustained depletion of circulating estradiol and progesterone is firmly established between three and six weeks post-surgery29. Consequently, the six-week post-ovariectomy interval employed in our protocol represents a pathophysiologically robust timeframe for modeling chronic postmenopausal estrogen deficiency.
Oxidative stress is a cornerstone mechanism underlying ISO-induced cardiotoxicity1. Supraphysiological catecholamine exposure accelerates auto-oxidation into adrenochromes, generates excessive ROS, disrupts redox-sensitive signaling cascades, and triggers membrane lipid peroxidation and contractile impairment. In our study, LIR treatment significantly lowered myocardial MDA concentrations compared with untreated ISO rats and promoted a significant recovery of LVEF at 48 hours, aligning with prior reports documenting the potent antioxidant and cardioprotective properties of LIR30. In contrast, myocardial GSH concentrations remained unaltered across groups.
Alongside oxidative damage, nitrosative stress has been increasingly implicated in the pathogenesis of TTS30,31. Excessive β₂-adrenergic receptor stimulation augments nitric oxide (NO) synthesis in cardiomyocytes; in the presence of abundant superoxide anions, NO rapidly reacts to form peroxynitrite (ONOO⁻), a potent reactive nitrogen species that induces protein tyrosine nitration, cellular inflammation, and myocardial energetic failure31,32. Under basal conditions, physiological myocardial NO production is predominantly regulated by endothelial nitric oxide synthase (eNOS), whereas pathological NO overproduction is driven by inducible nitric oxide synthase (iNOS). Notably, long-term ovariectomy shifts this enzymatic equilibrium toward heightened iNOS expression and diminished eNOS activity, lowering myocardial tolerance to stress33. In the present study, myocardial nitrate concentrations—an indirect indicator of tissue NO generation—were elevated following ISO administration and significantly suppressed by LIR treatment. Because direct measurements of myocardial peroxynitrite, 3-nitrotyrosine accumulation, and eNOS/iNOS isoform expression were not performed, our mechanistic inferences regarding nitrosative signaling remain indirect and grounded in established literature31,33.
Extensive preclinical and clinical literature supports the cardiovascular benefits of LIR across diverse disease states. In experimental diabetic cardiomyopathy and doxorubicin-induced cardiotoxicity, LIR enhances myocardial insulin sensitivity, activates adenosine monophosphate–activated protein kinase (AMPK) signaling, limits lipid peroxidation, reduces circulating and tissue MDA levels, and preserves ventricular contractility34,35. At the clinical level, landmark cardiovascular outcome trials such as the LEADER trial have established that GLP-1 receptor agonists significantly reduce major adverse cardiovascular events and cardiovascular mortality in patients with type 2 diabetes, mediated in part through favorable modulation of myocardial bioenergetics and vascular inflammation36. In our experimental design, LIR was administered beginning five days prior to ISO injection and continued for 48 hours post-insult, consistent with established cardioprotective pretreatment protocols against acute oxidative injury16. Although prophylactic administration does not mirror the unpredictable acute clinical onset of TTS, this regimen enables a rigorous evaluation of the preventive and molecular mechanisms by which GLP-1 receptor agonism counteracts catecholamine-induced cardiotoxicity. Future translational studies incorporating therapeutic (post-ISO) administration of LIR are warranted to evaluate its efficacy as an acute rescue therapy.
At the molecular level, SIRT1 is a critical NAD⁺-dependent deacetylase that orchestrates cellular stress resistance, mitochondrial quality control, and cardiomyocyte survival11. The AMPK/SIRT1/PGC-1α signaling axis serves as a central rheostat of mitochondrial homeostasis and myocardial redox balance37. Specifically, PGC-1α requires both AMPK-mediated phosphorylation and SIRT1-catalyzed deacetylation to achieve full transcriptional activity11. High-dose ISO exposure disrupts mitochondrial ultrastructure and suppresses mitochondrial biogenesis pathways during acute TTS-like injury38. In the present investigation, ISO administration markedly depleted myocardial SIRT1 and PGC-1α protein levels, whereas LIR treatment significantly restored the expression of both proteins (Figure 3). Because enzymatic deacetylase activity, downstream nuclear respiratory factor targets, and mitochondrial respiration were not directly assayed, these findings reflect preservation of protein abundance rather than definitive functional activation of the signaling cascade.
Nevertheless, our observations align closely with prior studies evaluating SIRT1 and PGC-1α protein expression in models of organ protection30,39,40. For instance, LIR has been shown to preserve mitochondrial architecture and mitigate oxidative stress via the SIRT1/SIRT3–FOXO3a pathway in non-alcoholic fatty liver disease41. Similarly, Zhang et al. demonstrated that LIR attenuates myocardial damage and pyroptosis in diabetic rats via activation of the SIRT1/AMPK pathway42. Furthermore, LIR pretreatment upregulates PGC-1α expression and promotes mitochondrial biogenesis to protect against gentamicin-induced acute kidney injury43. Collectively, these convergent lines of evidence support the hypothesis that preservation of the SIRT1/PGC-1α axis contributes to the cardioprotective actions of LIR during catecholamine overload.
Interestingly, although certain studies have reported LIR-mediated increases in tissue GSH concentrations30,35, we observed no significant differences in myocardial GSH levels among our experimental groups. This divergence may be attributable to dosing differences, as studies reporting GSH elevation frequently employed higher doses or longer durations of LIR treatment than the low, euglycemic dose (150 µg/kg/day for seven days) used here. Importantly, this 150 µg/kg/day regimen was sufficient to suppress lipid peroxidation (MDA), reduce nitrosative stress (nitrate), upregulate SIRT1/PGC-1α expression, and improve LVEF without inducing hypoglycemia. Mechanistically, PGC-1α coregulates endogenous antioxidant gene expression partly via nuclear factor erythroid 2–related factor 2 (Nrf2) signaling, and LIR has been shown to promote Nrf2 nuclear translocation to attenuate MDA accumulation30. Future investigations incorporating functional mitochondrial respirometry and downstream Nrf2/antioxidant enzyme assays are needed to fully validate these pathways.
Several limitations of the present study should be acknowledged. First, classical apical ballooning was not detected, likely reflecting the spatial and temporal resolution constraints of standard M-mode small-animal echocardiography under ketamine/xylazine anesthesia. Second, myocardial histopathological examination, direct mitochondrial functional assays, and apoptotic marker analyses were not performed. Third, our evaluation of oxidative and nitrosative stress was restricted to tissue MDA, GSH, and nitrate levels. Fourth, LIR was administered using a prophylactic pretreatment schedule rather than a post-injury therapeutic protocol. Finally, because only ovariectomized female rats were studied without a sham-operated non-ovariectomized control group, the specific interaction between estrogen deficiency and GLP-1 receptor agonism could not be independently dissected.
Conclusion
In an ovariectomized rat model of ISO-induced TTS-like cardiomyopathy, LIR treatment significantly attenuated myocardial lipid peroxidation and nitrosative stress—as evidenced by reduced tissue MDA and nitrate levels—while restoring myocardial SIRT1 and PGC-1α protein expression and improving left ventricular systolic function at 48 hours post-injury. These findings indicate that the cardioprotective effects of LIR against catecholamine-induced myocardial dysfunction are associated with modulation of redox balance and preservation of the SIRT1/PGC-1α signaling pathway. Future studies incorporating post-injury therapeutic dosing, sham-operated controls, and direct functional assessments of mitochondrial bioenergetics and apoptosis are warranted to further establish the translational potential of GLP-1 receptor agonists in stress-induced cardiomyopathy.
Declarations
Abbreviations
ANOVA: analysis of variance; AMPK: adenosine monophosphate–activated protein kinase; ATP: adenosine triphosphate; DTNB: 5,5′-dithiobis-(2-nitrobenzoic acid); ECG: electrocardiogram; ELISA: enzyme-linked immunosorbent assay; eNOS: endothelial nitric oxide synthase; GLP-1: glucagon-like peptide-1; GSH: reduced glutathione; HR: heart rate; iNOS: inducible nitric oxide synthase; i.p.: intraperitoneal; ISO: isoproterenol; IVSd: interventricular septal thickness in diastole; IVSs: interventricular septal thickness in systole; LIR: liraglutide; LVEF: left ventricular ejection fraction; LVPWd: left ventricular posterior wall thickness in diastole; LVPWs: left ventricular posterior wall thickness in systole; MDA: malondialdehyde; NAD⁺: nicotinamide adenine dinucleotide; NADPH: nicotinamide adenine dinucleotide phosphate; NO: nitric oxide; Nrf2: nuclear factor erythroid 2–related factor 2; OVX: ovariectomized; PBS: phosphate-buffered saline; PGC-1α: peroxisome proliferator-activated receptor γ coactivator-1α; ROS: reactive oxygen species; s.c.: subcutaneous; SD: standard deviation; SIRT1: sirtuin-1; TBARS: thiobarbituric acid reactive substances; TTS: Takotsubo syndrome.
Acknowledgments
This work was supported by the Scientific and Technological Research Council of Türkiye (TÜBİTAK) and Zonguldak Bülent Ecevit University. The authors gratefully acknowledge the financial and institutional support provided by these organizations.
Author’s contributions
Hale Sayan Özaçmak and Sefa Özduran conceived and designed the study. Sefa Özduran, Nazmiye Sultan Özduran, and Hale Sayan Özaçmak performed the animal experiments and surgical procedures. Naile Eriş Güdül and Ahmet Avcı performed the transthoracic echocardiographic assessments and data analysis. Hale Sayan Özaçmak and Sefa Özduran collected the tissue samples and conducted the biochemical and ELISA analyses. Hale Sayan Özaçmak and Sefa Özduran prepared the initial draft of the manuscript. Hale Sayan Özaçmak and Naile Eriş Güdül critically revised and edited the manuscript for important intellectual content. All authors read and approved the final manuscript.
Funding
This study was supported by the Scientific and Technological Research Council of Türkiye (TÜBİTAK; Project No. 1919B012327407) and the Zonguldak Bülent Ecevit University Scientific Research Projects Unit (Project No. 2024-26259946-04).
Availability of data and materials
The datasets used and/or analyzed during the current study are available from the corresponding author upon reasonable request.
Ethics approval and consent to participate
All experimental procedures involving animals were reviewed and approved by the Animal Ethics Committee of Zonguldak Bülent Ecevit University (Approval No. 2024-13-09/05) and were conducted in strict accordance with the National Institutes of Health (NIH) Guide for the Care and Use of Laboratory Animals. Consent to participate is not applicable (None).
Consent for publication
None.
Declaration of generative AI and AI-assisted technologies in the writing process
None.
Competing interests
The authors declare that they have no financial or personal competing interests that could have appeared to influence the work reported in this paper (None).